
The facial nerve is the principal motor nerve of the face. It controls the movement of all the muscles of facial expression, the muscles that work together to give us expressiveness. Paralysis – temporary or permanent – of its branches or of the entire nerve therefore causes significant asymmetry and functional problems (dry eyes because the eyelids cannot close, difficulty speaking because of paralysis of the corner of the lips, etc.).
Idiopathic facial palsy, known as Bell’s palsy, is a common cause of facial weakness, but diagnosis requires clinical assessment and consideration of other causes. Its origin is not fully understood, and viral factors have been discussed. Many people improve within six months, but recovery can take longer and some have persistent weakness. Automatic complete recovery by a fixed deadline should not be promised, nor should a general percentage be used to diagnose the cause in an individual.
Permanent paralysis is mainly due to:
- Injuries involving fractures of the temporal bone,
- Major facial injuries
- Neoplasms (neuromas, cholesteatomas, brain tumours, parotid tumours, etc.), with paralysis arising either from nerve infiltration or iatrogenically during their removal.
- Autoimmune diseases
- Metabolic disorders
Symptoms
1. Facial asymmetry.
2. Drooping of the eyebrow.
3. Loss of wrinkles on the forehead and cheeks.
4. Drooping of the corner of the mouth.
5. Uncontrolled tearing from the eye on the affected side.
6. Inability to close the eye on the affected side.
7. Inability to tighten the lip or keep food in the mouth.
8. Progressive atrophy of the facial muscles.
9. Loss of taste on the affected side.
Treatment
To be effective, conservative treatment must begin immediately or, at the latest, within the first three days after symptoms develop. Protecting the corneas with eye drops is important until eyelid closure is restored
Acupuncture has been studied as an additional intervention for Bell’s palsy, but the references do not establish universal restoration in one third of the time required by every other treatment. 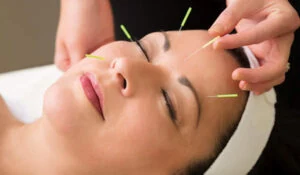 Study design, initial severity and usual care need examination. The review protocol in the bibliography describes planned research rather than completed results. Possible mechanisms discussed for electroacupuncture do not predict nerve recovery in an individual. Timely assessment, established treatment and eye protection remain necessary, with uncertainty discussed before complementary use. A favourable trial does not justify guaranteeing full recovery, faster recovery in every person or replacement of the treating clinician’s plan.
References
1. Li B, Sun X, Guo J, Shu W, Cheng Y, Li J. Effectiveness comparisons of acupuncture treatments for Bell palsy in adults: A protocol for systematic review and Bayesian network meta-analysis. Medicine (Baltimore). 2020;99(23).
2. Zhong, W., Yu, H., Rao, X., Wu, J., Gou, Y., Cui, H., Huang, X., & Wang, L. (2020). Efficacy of Manipulative Acupuncture Therapy Monitored by LSCI Technology in Patients with Severe Bell’s Palsy: A Randomized Controlled
Facial palsy: symptoms and assessment
Facial asymmetry and weakness cannot be interpreted from a photograph or general description. New symptoms need prompt medical assessment.
Explore Neurological disorders and symptoms or read how Medical Acupuncture Methods is presented at Satory.
Information source: NHS — Bell’s palsy and urgent assessment.
New facial weakness needs prompt assessment
A sudden change in facial movement cannot be diagnosed from a photograph or an online list of symptoms. Bell’s palsy is one possible cause, but other conditions must be considered. Facial weakness accompanied by arm weakness, speech difficulty or other sudden neurological symptoms requires emergency help. Searching for complementary appointments must not delay that assessment. Even when the problem appears limited to the face, early medical contact matters because treatment decisions depend partly on the timing and clinical findings.
Record the time symptoms started as accurately as possible. The clinician will assess the course, movement of the eyelids and mouth, and associated symptoms. Previous episodes, recent illnesses and current medication also belong in the history. A diagnosis does not follow simply from one side appearing weaker. Once the cause is assessed, advice is tailored to the individual situation. General information about possible causes cannot determine the right treatment or establish whether a particular person has idiopathic facial palsy.
Eye protection is a separate priority
When the eyelid does not close adequately, the eye surface needs specific protection advice. This may involve lubricating preparations and protection during sleep as directed by the clinician. Expecting facial movement to return soon is not sufficient protection. Eye pain, altered vision or increasing discomfort needs assessment. Eye care continues for as long as necessary and is not replaced by acupuncture or exercises found online. Ask for practical instructions if the method of using drops, ointment or other protection is unclear.
Recovery differs between people. Many improve within months, but not everyone recovers completely or within the same period. A general reference to six months is not an individual deadline or guarantee. If progress is not as expected, reassessment can address function, discomfort and possible rehabilitation needs. Effects on communication, work and confidence are legitimate parts of the discussion, alongside visible symmetry. Support should reflect the difficulties actually experienced rather than assuming the external appearance captures the whole impact of the condition.
Interpret acupuncture references carefully
A publication described as a protocol for a systematic review reports planned research rather than completed findings. It cannot by itself establish that acupuncture restores normal facial movement in one third of the time required by every other treatment. Interpretation must distinguish natural recovery, usual treatment and any additional intervention. Relevant trials need to describe initial severity, time since onset, comparison treatment and how recovery was measured. Without these details, a favourable summary can suggest more certainty than the research provides.
References to nerve regeneration in experimental settings do not predict facial movement in a particular person. If complementary acupuncture is considered, discuss uncertainty, technique and risks with the treating clinician’s knowledge. Timely established treatment and protection of the eye remain priorities. A session should not be presented as a way to avoid diagnosis, discontinue prescribed care or guarantee full restoration. Evidence about a possible biological process and evidence of a worthwhile clinical outcome are different questions.
Agree goals, review and cost
Before additional services, clarify which function will be monitored and when progress will be reviewed. Eating safely or closing the eye is different from a general feeling of wellbeing. Ask what the fee includes and whether reassessment is separate. An article cannot prescribe a universal number of sessions, and a price should never imply a guaranteed speed of recovery. Decisions can then be reconsidered against actual progress and the wider medical plan.
Sources for further information
Understanding pain and treatment goals
Can I assume by myself that this is Bell’s palsy?
No. New facial weakness needs prompt assessment. With limb weakness or speech difficulty, seek emergency help rather than waiting for a scheduled session.
What information helps a clinician assess pain?
Location, duration, intensity and effects on movement or sleep provide different information. Previous injuries, investigations and treatments already tried also help frame the discussion.